Complete cohort - Case 14 of 83
Case 17
Assigned out-of-fold recommendation
Coil embolization alone
Alternative: Balloon-assisted coil embolization
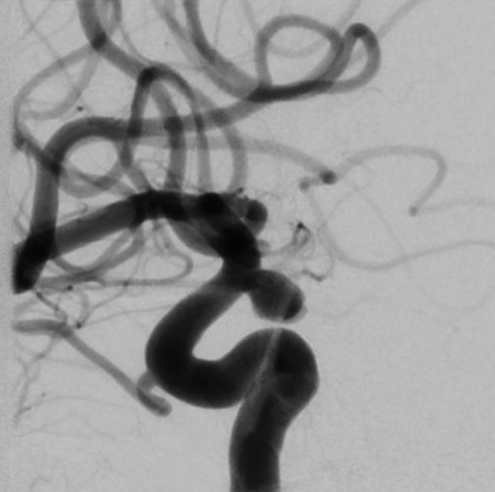
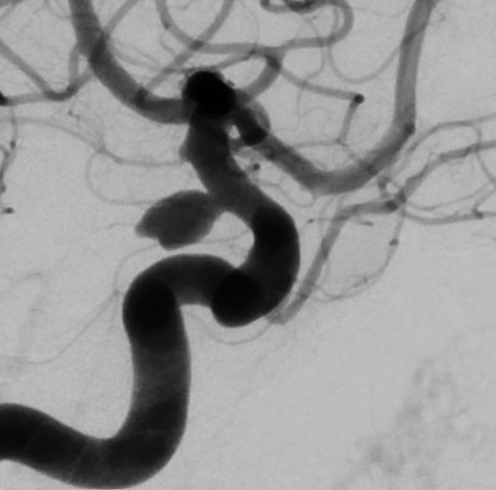
View A is AP; View B is lateral, as confirmed by the data provider.
Case summary
A 68-year-old female presented with a subarachnoid hemorrhage caused by a ruptured 8 mm x 5 mm x 5 mm saccular aneurysm with a 2.5 mm neck located at the right internal carotid artery communicating segment.
Image observation
On the supplied views, a saccular outpouching appears to project posteriorly from the right internal carotid artery communicating segment, with the anterior choroidal artery arising distal to the aneurysm neck.
Model-generated clinical rationale
The documented 2.5 mm neck width suggests a dome-to-neck ratio that may support coil embolization alone, as the neck is not explicitly described as wide. However, the aneurysm is located at the communicating segment, where the posterior communicating artery is noted to be absent or small, potentially limiting the need for balloon assistance to protect a major branch. The recommendation appears plausible but relies on the assumption that the neck is sufficiently narrow to maintain coil stability without adjunctive devices.
Model uncertainty
The OOF score distribution was diffuse: Coil embolization alone ranked first, but Balloon-assisted coil embolization remained a material alternative.
Clinical uncertainty / missing factor
The precise morphological characteristics of the aneurysm neck and the exact spatial relationship to the anterior choroidal artery origin are not fully defined, which limits the certainty of coil stability without balloon support.
Explicit evidence used
8 mm x 5 mm x 5 mm aneurysm with 2.5 mm neck | No clear appreciation of a posterior communicating artery