Complete cohort - Case 15 of 83
Case 18
Assigned out-of-fold recommendation
Flow diversion alone
Alternative: Coil embolization alone
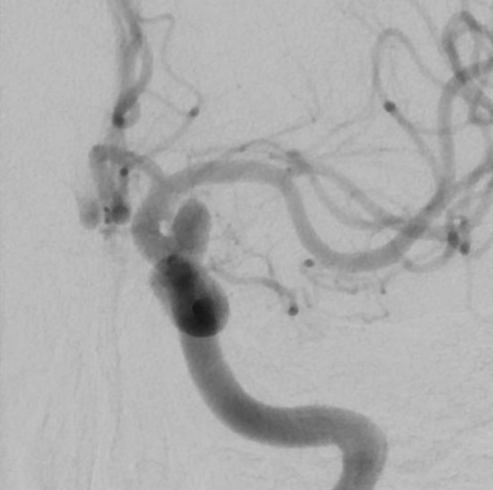
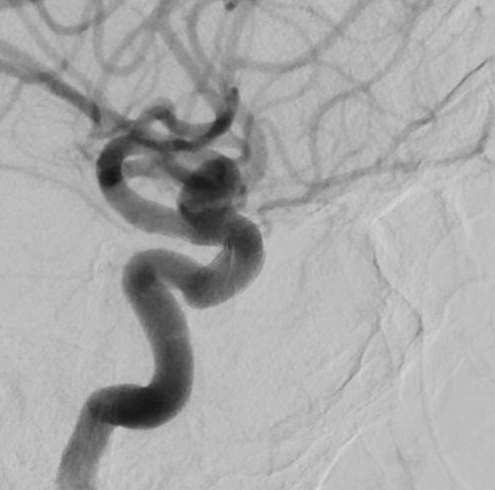
View A is AP; View B is lateral, as confirmed by the data provider.
Case summary
A 73-year-old female presents for elective treatment of a 6.9 mm unruptured left ophthalmic aneurysm with a wide 4.2 mm neck.
Image observation
On the supplied views, a saccular outpouching appears on the superior aspect of the internal carotid artery, with the ophthalmic artery arising separately from the neck.
Model-generated clinical rationale
The assigned recommendation of flow diversion is supported by the wide neck width, which may complicate coil retention. However, the separate origin of the ophthalmic artery introduces a risk of branch occlusion with a flow diverter, making the recommendation less definitive.
Model uncertainty
The OOF classifier scores for Flow diversion alone and Coil embolization alone were close, so the assigned recommendation should be treated as uncertain.
Clinical uncertainty / missing factor
The decision is limited by the lack of explicit documentation regarding the specific angle of the ophthalmic artery takeoff and the feasibility of preserving patency with a flow diverter.
Explicit evidence used
6.9 mm aneurysm with 4.2 mm wide neck | Ophthalmic artery originates separately from the aneurysm neck