
Cerebrovascular treatment research review
Multimodal treatment recommendation with auditable clinical reasoning.
The complete 83-case cohort combines preoperative clinical text with AP and lateral DSA views. Every case has an out-of-fold Top-1 and Top-2 recommendation, a model-generated rationale, and an explicit uncertainty statement.
Review methodology
Case evidence and review methodology
The technical pipeline covers all 83 cases. Blinded physician review remains the next validation step.
Data audit
83 de-identified cases were linked to 166 PNG images. Each case has one AP and one lateral view.
Leakage-controlled evaluation
Each case appeared in a held-out test fold exactly once across five folds.
Multi-reference scoring
Top-1 and Top-2 predictions were compared with all supplied expert references, preserving disagreement.
Reasoning generation
Qwen3.6-27B generated 83 case rationales from model outputs without receiving the reference labels.
Interpretation
Strong candidate coverage, limited exact agreement
Top-2 coverage is high when any expert reference is accepted. Exact agreement with the technique actually used remains modest, reflecting both model error and real treatment-choice variability.
Important limits
Not yet a clinical validation result
- No patient-to-case mapping was supplied; evaluation is case-level.
- No independent locked external cohort has been tested.
- Class scores have not been calibrated as probabilities of clinical correctness.
- Generated rationales still require blinded physician review.
Cohort organization
One primary grouping, three complementary views
Cases are grouped by the model's Top-1 technique and can be filtered by performance, score separation, and expert-reference agreement.
Primary groupingTop-1 technique
Coil embolization alone55
Stent-assisted coil embolization14
Flow diversion alone7
Balloon-assisted coil embolization3
Flow diversion with coil embolization3
Flow disruption (intra-saccular)1
PerformanceAny expert reference
61Top-1 matches any expert reference
15Top-2 adds a matching option
7Neither Top-1 nor Top-2 matches
UncertaintyTop-1 minus Top-2 score
44Clearer preference (margin >= 0.20)
20Intermediate (margin 0.10-0.20)
19High uncertainty (margin < 0.10)
Reference agreementFour expert labels
12Unanimous expert reference (4/4)
42Expert majority (3/4)
29Substantial expert disagreement
Complete cohort
All 83 de-identified cases
Use the filters to inspect recommendations, failure modes, uncertainty, and expert disagreement without changing the underlying case set.
83cases shown
Case 1Top-2 rescue
Coil embolization aloneAlternative: Stent-assisted coil embolizationView case detailsCase 5Top-1 hit
Coil embolization aloneAlternative: Stent-assisted coil embolizationView case detailsCase 6Top-1 hit
Coil embolization aloneAlternative: Balloon-assisted coil embolizationView case detailsCase 7Top-2 rescue
Coil embolization aloneAlternative: Flow diversion with coil embolizationView case detailsCase 8Top-1 hit
Flow diversion aloneAlternative: Flow diversion with coil embolizationView case detailsCase 9Top-1 hit
Coil embolization aloneAlternative: Stent-assisted coil embolizationView case detailsCase 10Top-2 rescue
Coil embolization aloneAlternative: Balloon-assisted coil embolizationView case detailsCase 11Top-2 rescue
Coil embolization aloneAlternative: Stent-assisted coil embolizationView case detailsCase 12Top-1 hit
Balloon-assisted coil embolizationAlternative: Coil embolization aloneView case detailsCase 13Top-1 hit
Flow diversion with coil embolizationAlternative: Stent-assisted coil embolizationView case detailsCase 14Top-1 hit
Stent-assisted coil embolizationAlternative: Flow disruption (intra-saccular)View case detailsCase 15Top-1 hit
Flow diversion aloneAlternative: Coil embolization aloneView case detailsCase 16Top-1 hit
Coil embolization aloneAlternative: Stent-assisted coil embolizationView case detailsCase 17Top-1 hit
Coil embolization aloneAlternative: Balloon-assisted coil embolizationView case detailsCase 18Top-1 hit
Flow diversion aloneAlternative: Coil embolization aloneView case detailsCase 19Top-1 hit
Balloon-assisted coil embolizationAlternative: Coil embolization aloneView case detailsCase 20Top-2 rescue
Flow disruption (intra-saccular)Alternative: Flow diversion aloneView case detailsCase 22Top-1 hit
Coil embolization aloneAlternative: Balloon-assisted coil embolizationView case detailsCase 23Top-1 hit
Coil embolization aloneAlternative: Stent-assisted coil embolizationView case detailsCase 24Top-1 hit
Coil embolization aloneAlternative: Balloon-assisted coil embolizationView case detailsCase 25Top-2 miss
Coil embolization aloneAlternative: Stent-assisted coil embolizationView case detailsCase 26Top-1 hit
Coil embolization aloneAlternative: Balloon-assisted coil embolizationView case detailsCase 27Top-1 hit
Flow diversion with coil embolizationAlternative: Flow diversion aloneView case detailsCase 28Top-1 hit
Stent-assisted coil embolizationAlternative: Flow disruption (intra-saccular)View case detailsCase 29Top-2 miss
Coil embolization aloneAlternative: Stent-assisted coil embolizationView case detailsCase 30Top-1 hit
Coil embolization aloneAlternative: Stent-assisted coil embolizationView case detailsCase 31Top-2 miss
Coil embolization aloneAlternative: Balloon-assisted coil embolizationView case detailsCase 32Top-1 hit
Coil embolization aloneAlternative: Balloon-assisted coil embolizationView case detailsCase 33Top-1 hit
Coil embolization aloneAlternative: Balloon-assisted coil embolizationView case detailsCase 37Top-1 hit
Coil embolization aloneAlternative: Balloon-assisted coil embolizationView case detailsCase 38Top-1 hit
Coil embolization aloneAlternative: Flow diversion aloneView case detailsCase 39Top-2 rescue
Stent-assisted coil embolizationAlternative: Coil embolization aloneView case detailsCase 41Top-1 hit
Coil embolization aloneAlternative: Balloon-assisted coil embolizationView case detailsCase 42Top-1 hit
Coil embolization aloneAlternative: Balloon-assisted coil embolizationView case detailsCase 44Top-1 hit
Coil embolization aloneAlternative: Flow diversion aloneView case detailsCase 45Top-1 hit
Coil embolization aloneAlternative: Flow diversion with coil embolizationView case detailsCase 46Top-1 hit
Coil embolization aloneAlternative: Flow diversion aloneView case detailsCase 47Top-2 rescue
Coil embolization aloneAlternative: Stent-assisted coil embolizationView case detailsCase 48Top-1 hit
Coil embolization aloneAlternative: Flow diversion aloneView case detailsCase 49Top-2 rescue
Coil embolization aloneAlternative: Flow diversion with coil embolizationView case detailsCase 50Top-1 hit
Coil embolization aloneAlternative: Flow diversion aloneView case detailsCase 51Top-1 hit
Coil embolization aloneAlternative: Stent-assisted coil embolizationView case detailsCase 52Top-2 rescue
Coil embolization aloneAlternative: Stent-assisted coil embolizationView case detailsCase 53Top-1 hit
Coil embolization aloneAlternative: Flow diversion with coil embolizationView case detailsCase 54Top-2 rescue
Coil embolization aloneAlternative: Stent-assisted coil embolizationView case detailsCase 55Top-1 hit
Stent-assisted coil embolizationAlternative: Coil embolization aloneView case detailsCase 56Top-2 miss
Coil embolization aloneAlternative: Balloon-assisted coil embolizationView case detailsCase 57Top-1 hit
Coil embolization aloneAlternative: Balloon-assisted coil embolizationView case detailsCase 58Top-2 rescue
Coil embolization aloneAlternative: Stent-assisted coil embolizationView case detailsCase 59Top-2 rescue
Stent-assisted coil embolizationAlternative: Coil embolization aloneView case detailsCase 60Top-1 hit
Stent-assisted coil embolizationAlternative: Coil embolization aloneView case detailsCase 61Top-1 hit
Coil embolization aloneAlternative: Flow diversion with coil embolizationView case detailsCase 62Top-2 rescue
Coil embolization aloneAlternative: Flow disruption (intra-saccular)View case detailsCase 64Top-2 rescue
Stent-assisted coil embolizationAlternative: Coil embolization aloneView case detailsCase 66Top-1 hit
Coil embolization aloneAlternative: Flow diversion with coil embolizationView case detailsCase 71Top-1 hit
Stent-assisted coil embolizationAlternative: Flow diversion aloneView case detailsCase 72Top-1 hit
Coil embolization aloneAlternative: Balloon-assisted coil embolizationView case detailsCase 73Top-1 hit
Coil embolization aloneAlternative: Stent-assisted coil embolizationView case detailsCase 74Top-1 hit
Balloon-assisted coil embolizationAlternative: Coil embolization aloneView case detailsCase 75Top-1 hit
Coil embolization aloneAlternative: Stent-assisted coil embolizationView case detailsCase 76Top-1 hit
Stent-assisted coil embolizationAlternative: Balloon-assisted coil embolizationView case detailsCase 77Top-1 hit
Coil embolization aloneAlternative: Stent-assisted coil embolizationView case detailsCase 78Top-1 hit
Coil embolization aloneAlternative: Balloon-assisted coil embolizationView case detailsCase 79Top-2 miss
Flow diversion aloneAlternative: Coil embolization aloneView case detailsCase 80Top-1 hit
Stent-assisted coil embolizationAlternative: Coil embolization aloneView case detailsCase 81Top-2 miss
Coil embolization aloneAlternative: Balloon-assisted coil embolizationView case detailsCase 82Top-1 hit
Coil embolization aloneAlternative: Balloon-assisted coil embolizationView case detailsCase 83Top-1 hit
Stent-assisted coil embolizationAlternative: Coil embolization aloneView case detailsCase 84Top-1 hit
Coil embolization aloneAlternative: Balloon-assisted coil embolizationView case detailsCase 85Top-1 hit
Coil embolization aloneAlternative: Flow diversion aloneView case detailsCase 86Top-1 hit
Flow diversion aloneAlternative: Coil embolization aloneView case detailsCase 87Top-1 hit
Flow diversion aloneAlternative: Coil embolization aloneView case detailsCase 88Top-1 hit
Coil embolization aloneAlternative: Stent-assisted coil embolizationView case detailsCase 89Top-1 hit
Stent-assisted coil embolizationAlternative: Coil embolization aloneView case detailsCase 90Top-1 hit
Stent-assisted coil embolizationAlternative: Coil embolization aloneView case detailsCase 91Top-1 hit
Flow diversion aloneAlternative: Coil embolization aloneView case detailsCase 93Top-1 hit
Coil embolization aloneAlternative: Balloon-assisted coil embolizationView case detailsCase 94Top-1 hit
Coil embolization aloneAlternative: Balloon-assisted coil embolizationView case detailsCase 95Top-1 hit
Flow diversion with coil embolizationAlternative: Flow diversion aloneView case detailsCase 96Top-1 hit
Coil embolization aloneAlternative: Flow diversion with coil embolizationView case detailsCase 97Top-2 rescue
Coil embolization aloneAlternative: Stent-assisted coil embolizationView case detailsCase 98Top-2 miss
Stent-assisted coil embolizationAlternative: Flow diversion aloneView case detailsCase 100Top-1 hit
Coil embolization aloneAlternative: Balloon-assisted coil embolizationView case detailsBlinded qualitative physician review
16 selected de-identified cases
Selected to cover confident, ambiguous, adjunctive-device, and retreatment scenarios. Outcome groups and expert-reference agreement are intentionally hidden in this section.
Review progress0 / 16
Ratings are stored only in this browser until exported.
Review case 1 of 16
Case 61
Awaiting review
Assigned out-of-fold recommendation
Coil embolization alone
Alternative: Flow diversion with coil embolization
Top-1 class score73.9%
Top-2 class score10.4%
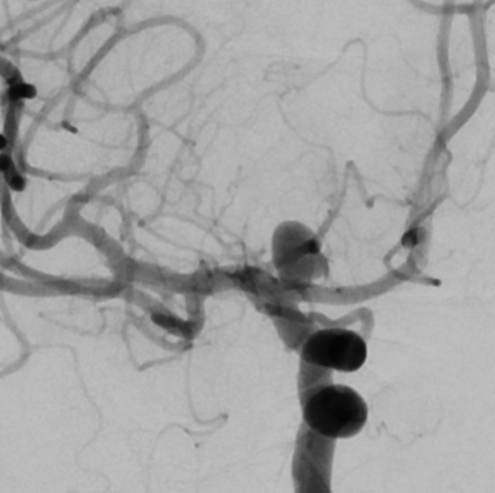
View A - APOpen full size
View B - LateralOpen full size
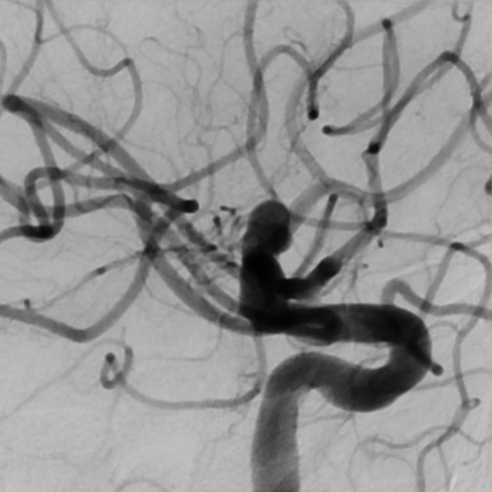
View A is AP; View B is lateral, as confirmed by the data provider.
Case summary
A 75-year-old male presents with an unruptured right ACA A1 aneurysm measuring 5.3 mm x 4 mm x 5.4 mm with a 3.1 mm neck and a daughter sac.
Image observation
On the supplied views, a saccular outpouching appears on the proximal anterior cerebral artery with a visible neck connecting to the parent vessel.
Model-generated clinical rationale
The documented dimensions and neck width suggest a morphology that may be amenable to endovascular coiling. However, the presence of a daughter sac and the specific neck-to-dome ratio are critical factors that are not fully quantified in the narrative, potentially complicating coil stability.
Model uncertainty
The OOF classifier showed a relatively clear preference for Coil embolization alone over Flow diversion with coil embolization, but its scores are not probabilities of clinical correctness.
Clinical uncertainty / missing factor
The precise neck-to-dome ratio and the exact relationship of the daughter sac to the aneurysm neck are missing, which are essential for determining the feasibility of coil-only treatment versus adjunctive techniques.
Explicit evidence used
Unruptured right ACA A1 aneurysm | Dimensions 5.3 mm x 4 mm x 5.4 mm with 3.1 mm neck | Presence of a daughter sac