Complete cohort - Case 79 of 83
Case 95
Assigned out-of-fold recommendation
Flow diversion with coil embolization
Alternative: Flow diversion alone
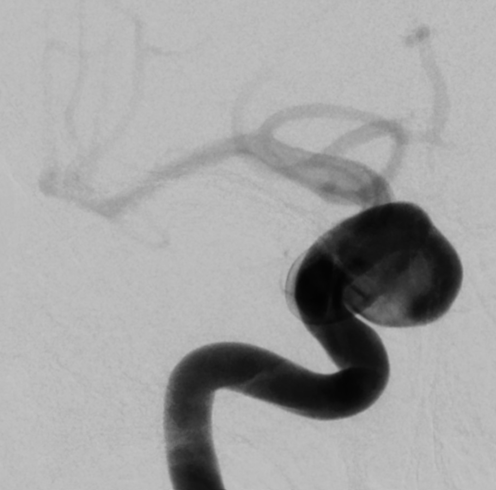
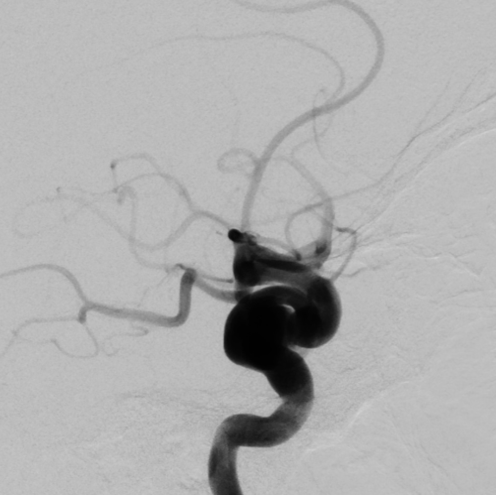
View A is AP; View B is lateral, as confirmed by the data provider.
Case summary
A 72-year-old female presents for elective treatment of a 1.3 cm medially projecting spherical aneurysm arising from the posterior cavernous segment of the right internal carotid artery.
Image observation
On the supplied views, a large, contrast-filled saccular outpouching appears to arise from the tortuous internal carotid artery, with visible distal intracranial branching.
Model-generated clinical rationale
The assigned recommendation of flow diversion with coil embolization is supported by the aneurysm's large 1.3 cm size and spherical morphology, which may benefit from adjunctive coiling to promote thrombosis. However, the cavernous location and lack of documented wide-neck geometry or branch incorporation limit the certainty of this approach over flow diversion alone.
Model uncertainty
The OOF classifier scores for Flow diversion with coil embolization and Flow diversion alone were close, so the assigned recommendation should be treated as uncertain.
Clinical uncertainty / missing factor
The most significant missing decision factor is the precise neck-to-dome ratio and the presence of any critical branch vessels arising from the aneurysm neck.
Explicit evidence used
1.3 cm medially projecting spherical aneurysm | posterior cavernous internal carotid artery segment