Complete cohort - Case 80 of 83
Case 96
Assigned out-of-fold recommendation
Coil embolization alone
Alternative: Flow diversion with coil embolization
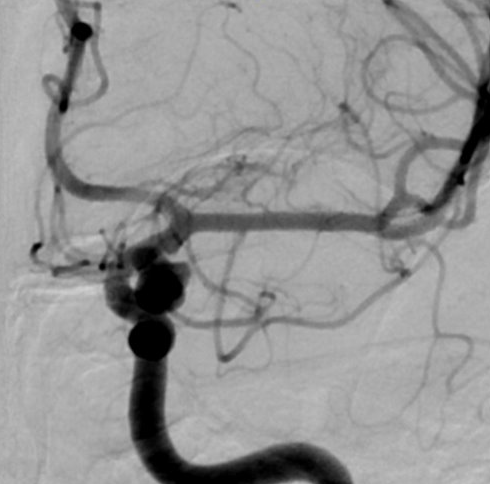
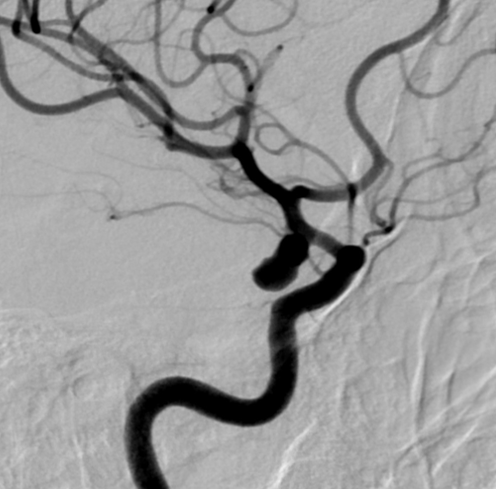
View A is AP; View B is lateral, as confirmed by the data provider.
Case summary
A 45-year-old female presents with headaches and a known unruptured 7 mm bilobed left communicating segment aneurysm with a 3 mm neck.
Image observation
On the supplied views, a bilobed aneurysmal sac appears to project laterally and inferiorly from the internal carotid artery, with the anterior choroidal artery visible nearby.
Model-generated clinical rationale
The assigned recommendation of coil embolization alone is supported by the documented 3 mm neck width, which suggests a geometry potentially amenable to endosaccular packing. However, the bilobed morphology and the proximity of the anterior choroidal artery may complicate coil stability or require adjunctive balloon assistance. The recommendation is limited by the lack of explicit documentation regarding the aneurysm's orientation relative to the parent vessel flow.
Model uncertainty
The OOF score distribution was diffuse: Coil embolization alone ranked first, but Flow diversion with coil embolization remained a material alternative.
Clinical uncertainty / missing factor
The most significant missing decision factor is the precise relationship between the aneurysm neck and the origin of the anterior choroidal artery, which is critical for determining the safety of coil-only treatment.
Explicit evidence used
7 mm X 7 mm bilobed communicating segment aneurysm | 3mm neck projecting laterally, inferiorly and posteriorly