Complete cohort - Case 81 of 83
Case 97
Assigned out-of-fold recommendation
Coil embolization alone
Alternative: Stent-assisted coil embolization
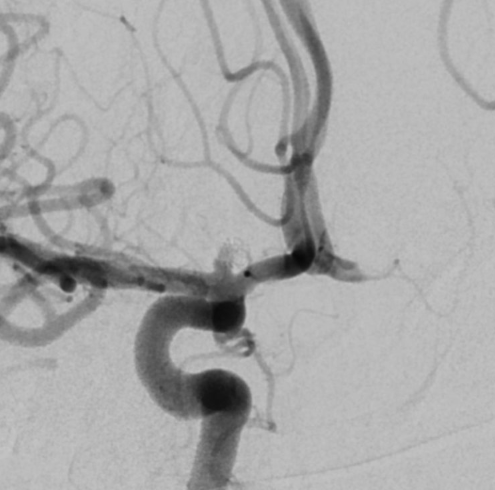
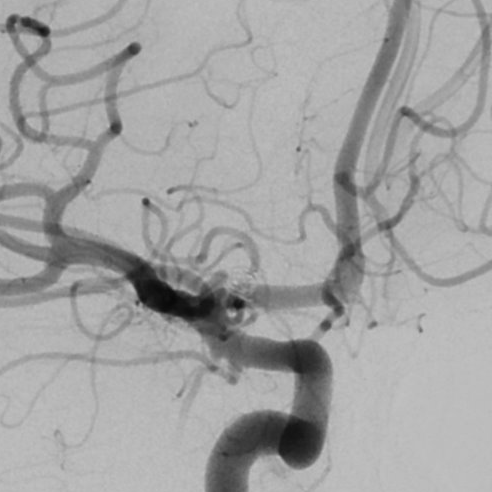
View A is AP; View B is lateral, as confirmed by the data provider.
Case summary
A 41-year-old patient presents with a recurrent right ICA terminus aneurysm, measuring 1.3mm x 2mm, following a prior subarachnoid hemorrhage.
Image observation
On the supplied views, the aneurysm appears as a small, anteriorly projecting outpouching at the ICA bifurcation with a visible mass of prior treatment material at the dome.
Model-generated clinical rationale
The assigned recommendation of coil embolization alone is supported by the small dimensions of the residual aneurysm and the presence of prior treatment material which may provide a scaffold. However, the recurrent nature of the lesion and the terminus location often necessitate adjunctive devices to ensure stability, making the choice of standalone coiling potentially limited by the risk of recurrence.
Model uncertainty
The OOF classifier scores for Coil embolization alone and Stent-assisted coil embolization were close, so the assigned recommendation should be treated as uncertain.
Clinical uncertainty / missing factor
The specific morphology of the aneurysm neck and the exact configuration of the prior treatment mass are not fully defined, which are critical factors for determining the feasibility of standalone coiling versus stent assistance.
Explicit evidence used
1.3mm x 2mm residual ICA aneurysm | prior treatment mass seen at the dome