Complete cohort - Case 34 of 83
Case 42
Assigned out-of-fold recommendation
Coil embolization alone
Alternative: Balloon-assisted coil embolization
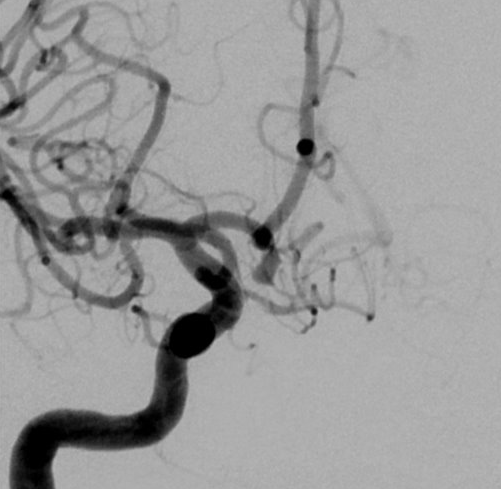
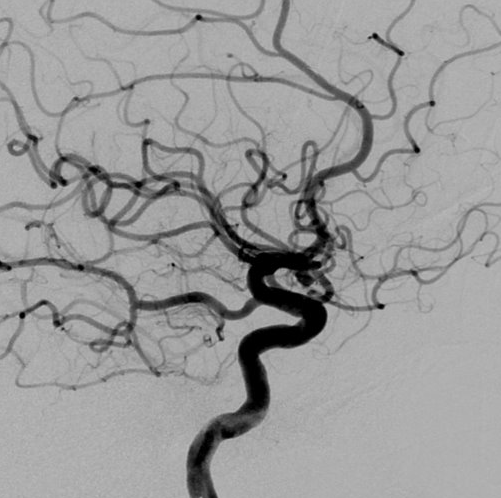
View A is AP; View B is lateral, as confirmed by the data provider.
Case summary
A 59-year-old female presented with subarachnoid hemorrhage and was found to have a 5mm x 2.3mm x 2.6mm ACOM aneurysm with dome irregularity.
Image observation
On the supplied views, the aneurysm appears as a distinct outpouching at the anterior communicating artery complex with adjacent branching vessels visible.
Model-generated clinical rationale
The assigned recommendation of coil embolization alone is supported by the aneurysm's small dimensions and the lack of documented branch vessel incorporation. However, the reported dome irregularity and the proximity to the anterior communicating artery junction may complicate coil stability. The recommendation is limited by the inability to confirm the neck-to-dome ratio or precise branch relationships from the provided data.
Model uncertainty
The OOF classifier scores for Coil embolization alone and Balloon-assisted coil embolization were close, so the assigned recommendation should be treated as uncertain.
Clinical uncertainty / missing factor
The precise neck width and the exact relationship of the aneurysm to the A2 segments are not explicitly defined, which are critical factors for determining the need for balloon assistance.
Explicit evidence used
5mm x 2.3mm x 2.6mm ACOM aneurysm | irregularity at the dome