Complete cohort - Case 35 of 83
Case 44
Assigned out-of-fold recommendation
Coil embolization alone
Alternative: Flow diversion alone
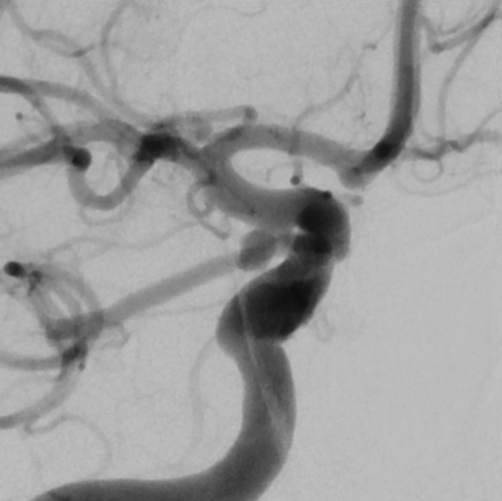
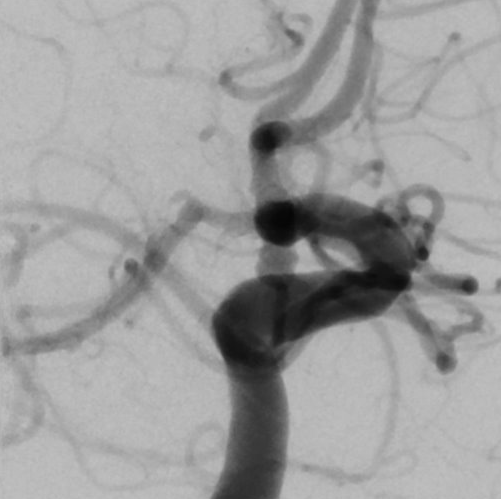
View A is AP; View B is lateral, as confirmed by the data provider.
Case summary
A 69-year-old female presents with a 4.4 mm x 3.6 mm x 2.9 mm right posterior communicating artery aneurysm with a fetal PCA originating from the neck.
Image observation
On the supplied views, a saccular outpouching appears at the posterior communicating artery junction with a visible vessel arising from the aneurysm neck.
Model-generated clinical rationale
The assigned recommendation of coil embolization alone is supported by the aneurysm's small dimensions and unruptured status. However, the presence of a fetal PCA originating from the neck complicates the procedure, as preserving this branch is critical to prevent ischemia. The model's preference for coiling is less definitive given the potential difficulty in maintaining patency of the fetal PCA during coil packing.
Model uncertainty
The OOF score distribution was diffuse: Coil embolization alone ranked first, but Flow diversion alone remained a material alternative.
Clinical uncertainty / missing factor
The most significant missing factor is the precise anatomical relationship between the fetal PCA origin and the aneurysm neck, which determines the feasibility of safe coil placement.
Explicit evidence used
4.4 mm x 3.6 mm x 2.9 mm right posterior communicating irregular aneurysm | fetal PCA originating from the aneurysm neck