Complete cohort - Case 36 of 83
Case 45
Assigned out-of-fold recommendation
Coil embolization alone
Alternative: Flow diversion with coil embolization
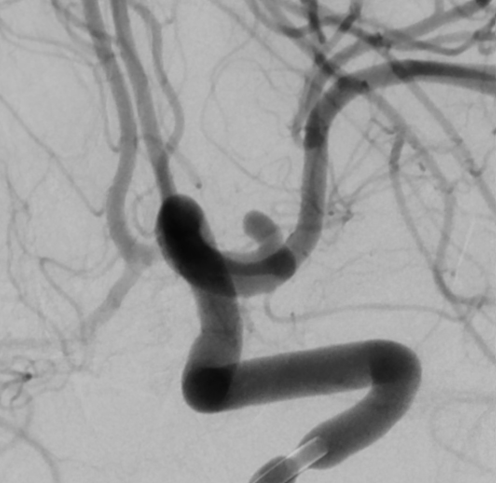
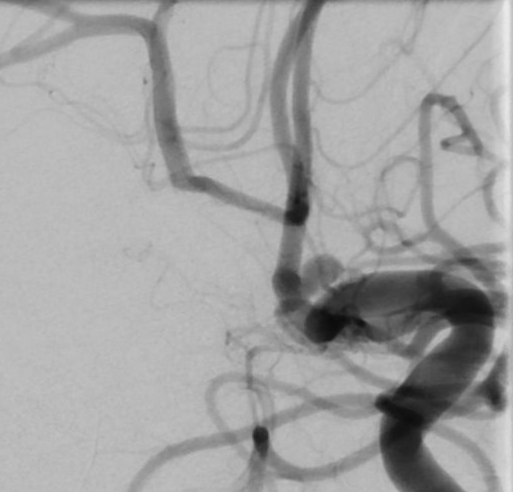
View A is AP; View B is lateral, as confirmed by the data provider.
Case summary
A 47-year-old female presents with an unruptured, anteriorly projecting, broad-based saccular aneurysm of the left A1 segment measuring 4.8 x 3.9 x 3.5 mm.
Image observation
On the supplied views, a saccular outpouching appears to arise from the proximal anterior cerebral artery, with the vessel course and caliber appearing patent.
Model-generated clinical rationale
The assigned recommendation of coil embolization alone is supported by the aneurysm's small dimensions and unruptured status. However, the documented broad-based morphology and slight dysplasia at the neck may present technical challenges for coil retention without adjunctive devices. The recommendation appears limited by the lack of specific neck-to-dome ratio data required to definitively assess coil stability.
Model uncertainty
The OOF classifier showed a relatively clear preference for Coil embolization alone over Flow diversion with coil embolization, but its scores are not probabilities of clinical correctness.
Clinical uncertainty / missing factor
The most significant missing decision factor is the precise neck width and dome-to-neck ratio, which are critical for determining the feasibility of coil-only treatment versus the need for flow diversion.
Explicit evidence used
Unruptured left A1 segment aneurysm | Broad-based morphology measuring 4.8 x 3.9 x 3.5 mm