Complete cohort - Case 20 of 83
Case 24
Assigned out-of-fold recommendation
Coil embolization alone
Alternative: Balloon-assisted coil embolization
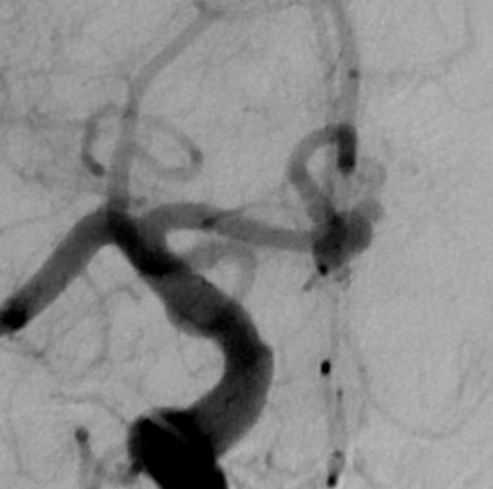
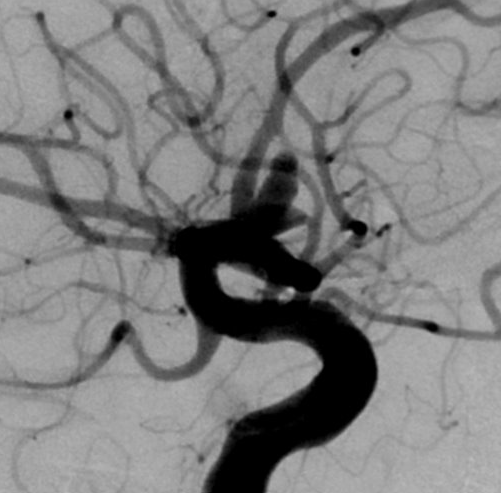
View A is AP; View B is lateral, as confirmed by the data provider.
Case summary
A 65-year-old male presented with subarachnoid hemorrhage and was found to have a complex, bilobed, wide-neck anterior communicating artery aneurysm with a small daughter sac.
Image observation
On the supplied views, the aneurysm appears as a contrast-filled outpouching at the anterior communicating artery junction with a wide neck and irregular contour.
Model-generated clinical rationale
The assigned recommendation of coil embolization alone is supported by the aneurysm's small dimensions (largest lobe 5.7 mm) and the presence of a daughter sac, which may favor endovascular management. However, the documented wide neck and bilobed morphology typically necessitate balloon assistance or stenting to maintain coil stability, making the recommendation of coils alone potentially questionable without further anatomical clarification.
Model uncertainty
The OOF classifier showed a relatively clear preference for Coil embolization alone over Balloon-assisted coil embolization, but its scores are not probabilities of clinical correctness.
Clinical uncertainty / missing factor
The most significant missing decision factor is the precise neck-to-dome ratio and the specific orientation of the aneurysm neck relative to the parent vessel, which are critical for determining the feasibility of unassisted coiling.
Explicit evidence used
5.7 mm bilobed wide-neck aneurysm | Small daughter sac on larger lobe