Complete cohort - Case 39 of 83
Case 48
Assigned out-of-fold recommendation
Coil embolization alone
Alternative: Flow diversion alone
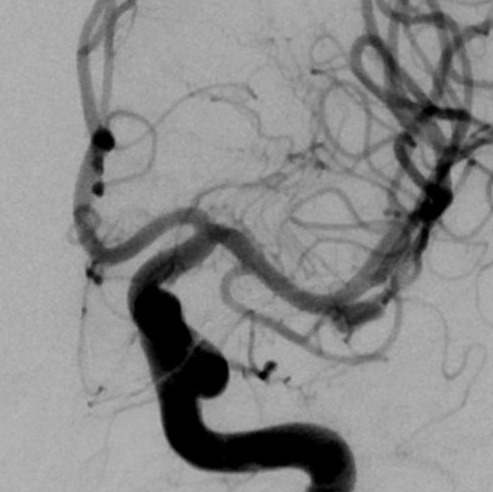
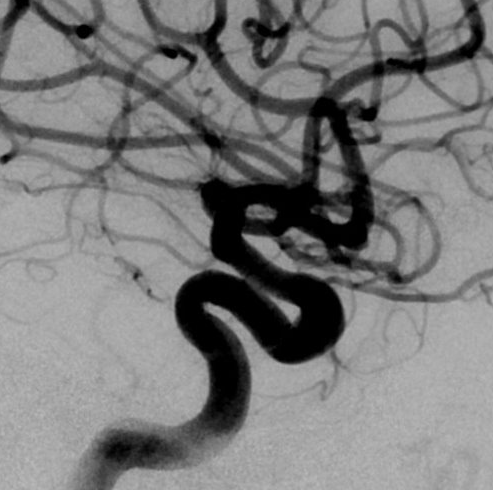
View A is AP; View B is lateral, as confirmed by the data provider.
Case summary
A 56-year-old female presents with an incidentally discovered 3.7mm x 2mm x 2mm unruptured left MCA bifurcation aneurysm and fibromuscular dysplasia.
Image observation
On the supplied views, a saccular outpouching appears at the MCA bifurcation with a visible neck, while the parent vessel and distal branches appear patent.
Model-generated clinical rationale
The assigned recommendation of coil embolization is supported by the aneurysm's small size and the documented 1.5mm neck, which may allow for stable coil packing. However, the bifurcation location presents a risk of branch occlusion, and the presence of fibromuscular dysplasia suggests vessel wall irregularities that could complicate catheter navigation or device stability.
Model uncertainty
The OOF score distribution was diffuse: Coil embolization alone ranked first, but Flow diversion alone remained a material alternative.
Clinical uncertainty / missing factor
The most significant missing decision factor is the precise morphological assessment of the neck-to-dome ratio and the exact angle of the bifurcation branches, which are critical for determining the feasibility of endovascular access and coil retention.
Explicit evidence used
3.7mm x 2mm x 2mm tear drop shaped aneurysm | 1.5mm neck projecting laterally from the bifurcation