Complete cohort - Case 42 of 83
Case 51
Assigned out-of-fold recommendation
Coil embolization alone
Alternative: Stent-assisted coil embolization
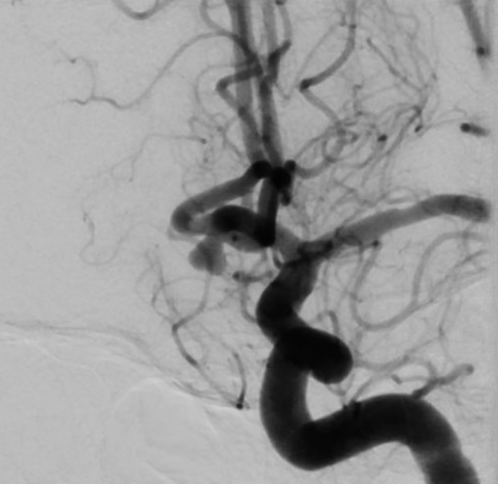
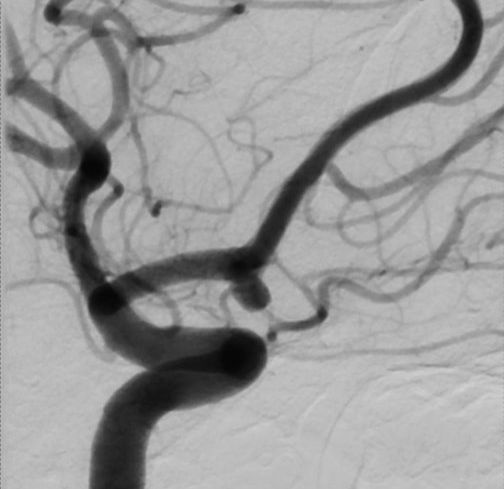
View A is AP; View B is lateral, as confirmed by the data provider.
Case summary
A 61-year-old female presents with an incidental, unruptured anterior communicating artery aneurysm measuring 4.3 x 3.9 x 2.9 mm with a 2.0 mm neck.
Image observation
On the supplied views, a saccular outpouching appears at the anterior communicating artery junction, with contrast filling the contralateral anterior cerebral artery.
Model-generated clinical rationale
The assigned recommendation of coil embolization alone is supported by the documented 2.0 mm neck width, which suggests a potentially favorable neck-to-dome ratio for primary coiling. However, the recommendation is limited by the lack of explicit documentation regarding the aneurysm's orientation or the presence of critical perforators, which are critical determinants for avoiding stent assistance.
Model uncertainty
The OOF score distribution was diffuse: Coil embolization alone ranked first, but Stent-assisted coil embolization remained a material alternative.
Clinical uncertainty / missing factor
The most significant missing decision factor is the precise morphological orientation of the aneurysm relative to the parent vessel, which is required to definitively assess the risk of coil prolapse.
Explicit evidence used
Aneurysm dimensions 4.3 x 3.9 x 2.9 mm | Neck width 2.0 mm